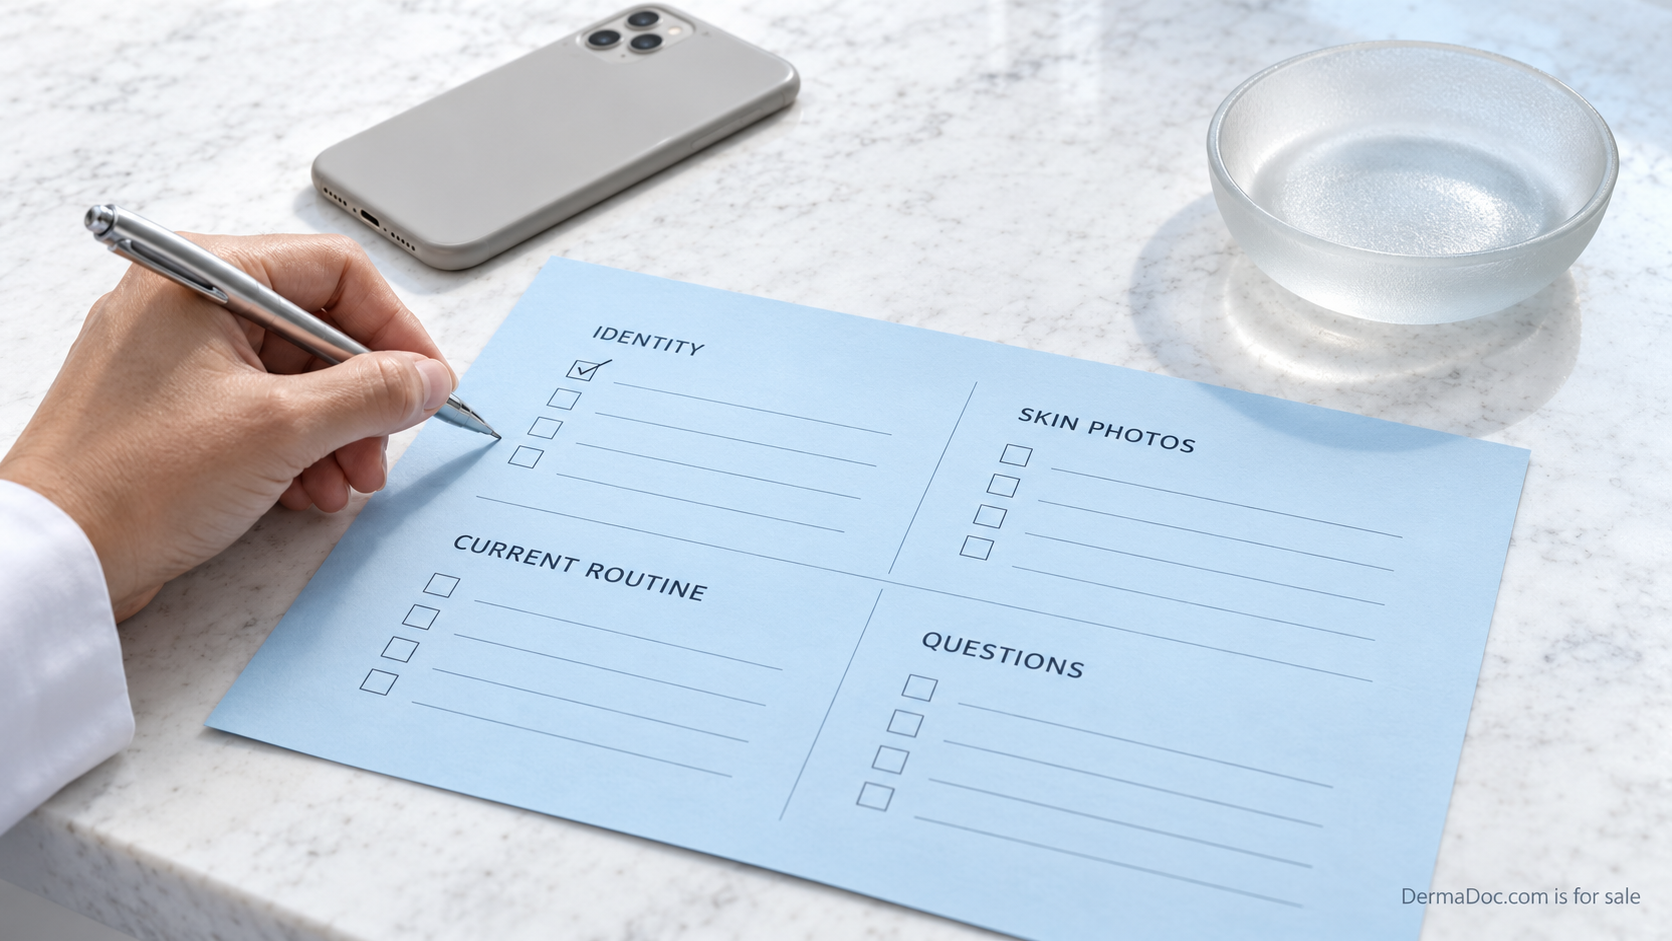
Remote skin-consult products often launch with a beautiful UI and an intake that asks the wrong questions in the wrong order. The result is confusion: visitors outside served markets complete clinical forms, support invents advice in chat, and marketing promises diagnosis the care model does not provide. This Journal guide sketches an honest first-consult intake. It is illustrative. Requirements vary by market. It is not medical advice and not legal advice.
Decide what the intake is for
Write one sentence that names the job. Example: "Collect enough information to decide whether this person can enter our consult workflow in a market we serve." If your sentence promises diagnosis from a photo upload, stop and revisit the care model with clinical leadership. Marketing pages and intake forms should share the same sentence.
Separate marketing CTA language from clinical documentation. The public button may say "Request a consult." The clinical record lives elsewhere under your compliance program. Do not blur those systems in the browser for convenience.
Field checklist (illustrative)
- Identity basics: name, preferred contact, date of birth if required by your model.
- Location early: state/country and enough detail to gate eligibility.
- Eligibility confirmation: plain language about where you serve.
- Reason for contact: free text with guidance, not a self-diagnosis quiz dressed as science.
- Urgency screen: redirect emergencies to local urgent or emergency care.
- Photo upload (optional): only if policy covers storage, access, and retention.
- Medication and allergy notes if your clinicians require them for the visit type.
- Consent and privacy acknowledgements with readable links.
- Scheduling preference or callback window.
- How they heard about you (optional, for ops, not for fake scarcity).
Order matters. Location and urgency should precede deep history. Photo upload should never be the first field. If a visitor fails eligibility, show a clear exit rather than a soft dead end that still stores clinical detail you cannot use.
Jurisdiction notes without false certainty
Licensure and telehealth rules differ by jurisdiction and change. Build a living map owned by clinical ops and counsel. The public site should state served areas in ordinary language and avoid "available everywhere" theater. Geo tools help but are imperfect; still ask the visitor.
When expanding markets, update intake and ads in the same release. A landing page that says two states while ads imply nationwide is an intake bug, not a growth hack. For general consumer protection orientation in the US, review current FTC guidance on advertising and endorsements alongside your state board rules. Primary sources beat blog summaries when stakes are high.
Conditional UI that behaves
Test computed visibility, not only HTML hidden attributes. Out-of-market visitors should not be required to complete clinical photo fields. In-market visitors should not be blocked by a leftover platform field from another form. Keyboard order should match what sighted users see. Error messages should retain entered data without stuffing secrets into the URL.
Those interaction rules sound like software hygiene because they are. They also reduce accidental collection. If you do not need a field for the active path, do not require it.
Copy guardrails inside the flow
- Prefer "request" and "schedule" over "diagnose" and "cure."
- State typical response windows as ranges, not guarantees.
- Explain what happens after submit in three steps maximum.
- Provide a human support path that refuses clinical improvisation.
- Keep emergency redirection visible on every long form page.
Worked example: mapping a noisy form
A startup form asks for twenty clinical fields before ZIP code, then promises "AI diagnosis in minutes." Mapping to this checklist would move location and urgency first, delete the diagnosis promise, shrink optional fields, and route emergencies out. Completion rate may drop. Eligibility quality usually rises. That trade is the point.
Ops metrics that do not invent outcomes
Track: start-to-complete rate, eligibility exit rate, photo upload failure rate, time to first clinician review, and out-of-market ad clicks. Do not track or publish invented cure percentages from incomplete intakes. Do not A/B test miracle headlines against careful ones as if conversion alone were the ethical scoreboard.
Vendor and privacy basics
List every processor that touches intake data. Confirm retention and deletion paths. Confirm who can view photos. Confirm whether marketing tools are blocked from clinical payloads. A pretty form that leaks uploads into a generic analytics bucket is not an honest intake.
If you reference consumer rights or health privacy regimes, link the regime that actually applies and avoid copying another company's notice. Accuracy beats length.
Ninety-minute internal workshop
- Print the live form.
- Label each field: required, optional, or remove.
- Mark where location and urgency appear.
- Rewrite three weak microcopy lines.
- Assign an owner for the licensure map update.
- Schedule a retest on keyboard-only navigation.
Photo handling without casual risk
If photos are part of intake, write the why before the upload widget. Clinicians should be able to say what decision the image supports. Storage should be limited, access logged, and retention defined. Thumbnails in support inboxes are a common leak. Prefer systems designed for clinical media over generic form tools when your model requires images.
Tell visitors what good photo conditions are without sounding like a diagnosis tutorial. Lighting and framing tips are logistics. Interpreting lesions is not a marketing job. If a photo is poor, ask for a retake rather than guessing in chat.
When a visitor declines photos, have a path that still respects the care model. Do not punish decline with invented urgency. Honest intake includes the right to withhold images the process does not truly need yet.
Support macros that refuse improvisation
Write five macros before launch: eligibility no, photo retake, emergency redirect, callback scheduling, and "I cannot give clinical advice in chat." Train contractors on the same list. Intake quality collapses when chat reinvents diagnosis after the form stayed careful.
Record when macros are used. Spikes in eligibility-no after a campaign usually mean ads and landing pages drifted. Fix the campaign before widening the form.
Next step: map your current form to this checklist. If you are evaluating DermaDoc.com for a remote consult brand, read the telederm Idea and inquire with markets and licensure plan. Purchase paths here are GoDaddy or Escrow.com. This article does not authorize a care model.